How do you define the anion gap?
The anion gap is a computed value that enables clinicians assess the equilibrium of electrolytes in the blood. It is usually derived from the main ions measured on a basic metabolic panel, especially sodium, chloride, and bicarbonate. Because routine lab tests do not measure every charged particle in the blood, the anion gap suggests the amount of unmeasured anions present.
In plain terms, the anion gap helps indicate whether something is missing from the expected acid-base balance. A low or high result does not confirm a condition by itself, but it acts as an useful diagnostic clue in the emergency setting. That is why an anion gap calculator is often used as soon as blood chemistry results are available.
The calculation is often based on the difference between positively charged sodium and the combination of chloride plus bicarbonate. Since bicarbonate is a key buffer, changes in its level often signal a metabolic derangement that needs rapid attention. Emergency clinicians use this value to identify an acid-base disorder before the cause is fully known.
The reason ED clinicians use an anion gap calculator
Emergency medicine relies on fast clinical pattern spotting. The anion gap calculator assists clinicians quickly decide whether a patient may have metabolic acidosis, a potentially dangerous form of acidemia that can https://anion-gap-calculation.com/reference/glossary.html occur in critical illness. It is not just a number; it is a tool for clinical decision-making.
If a patient presents with confusion, rapid breathing, hypotension, or suspected toxin exposure, the anion gap can focus the differential diagnosis. Combined with an arterial blood gas and a basic metabolic panel, it helps determine whether the patient has a primary acid-base problem and whether compensation is appropriate. The result can influence triage, the need for repeat labs, and whether advanced critical care support is needed.
The anion gap is especially helpful because it can provide a quicker signal than waiting for a complete workup. If the anion gap is elevated, clinicians may immediately consider lactic acid elevation, ketone production, renal dysfunction, or toxic ingestion. If it is normal, they may shift attention to bicarbonate loss, chloride excess, or a mixed process. That rapid sorting makes the tool valuable in the first minutes of evaluation.
High anion gap compared with standard anion gap: what is the difference?
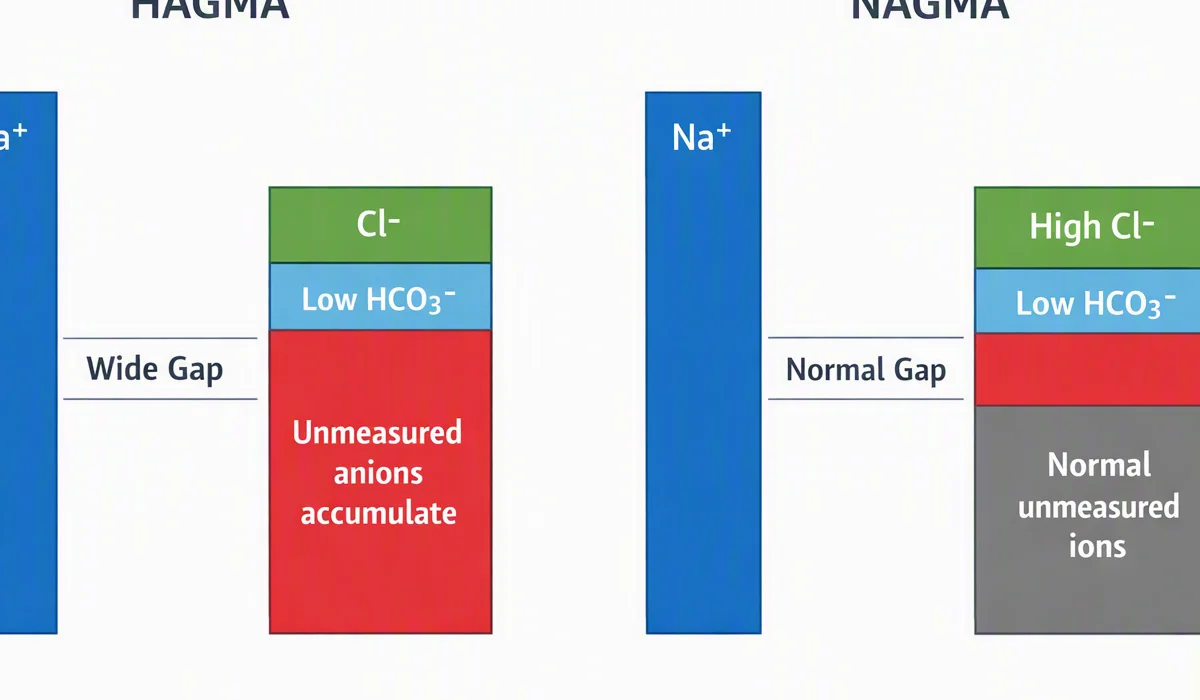
A elevated anion gap implies that additional acids or acid-related compounds are accumulating in the blood. This often happens when there is greater production of acids or limited clearance of them. Common causes include lactic acidosis, ketoacidosis, and renal failure.
In lactic acidosis, excess lactate rises when tissues do not receive sufficient oxygen or are unable to use oxygen effectively. In ketoacidosis, the body generates ketones when it cannot use glucose effectively. In renal failure, acid removal is reduced, which allows acid compounds to accumulate.
A normal anion gap, sometimes called a non-gap metabolic acidosis, usually points to bicarbonate loss with a compensatory rise in chloride. This is frequently called hyperchloremic acidosis. In this pattern, the blood may still be acidic, but the missing bicarbonate is replaced by chloride rather than by unmeasured acids. That difference is important because it changes the likely etiology and next tests.
Emergency clinicians rely on the distinction between high and normal anion gap to guide the workup quickly. A high gap often signals acid accumulation from severe systemic disease or toxin exposure, while a normal gap may suggest gastrointestinal bicarbonate loss or renal tubular problems. In both cases, the anion gap is not the final answer, but it helps determine the direction of the search.
Frequent emergency causes of an elevated anion gap
A number of urgent conditions can cause an elevated anion gap, and some require immediate treatment. Amongst the most important are sepsis, shock, toxic alcohols, and salicylate poisoning. Each can create a critical metabolic state that calls for rapid recognition.
Sepsis can lead to lactic acid buildup when infection leads to poor perfusion and impaired oxygen delivery. Shock from any cause can do the same because of tissue hypoperfusion, which raises anaerobic metabolism and lactate production. In these settings, the anion gap may be an early warning sign that the patient is deteriorating even before the full picture is clear.
Toxic alcohols such as methanol or ethylene glycol can produce a marked high anion gap through toxic metabolites. These cases are time-sensitive, and early lab interpretation may be the first clue that a poisoning is present. Salicylate poisoning can also produce an elevated gap and a complex acid-base pattern, sometimes including respiratory alkalosis and metabolic acidosis together.
Because these causes are potentially life-threatening, an increased anion gap should prompt immediate attention to the patient’s symptoms, vital signs, and exposure history. The Anion Gap Calculator helps clinicians move from a vague complaint to a focused list of dangerous possibilities.
How to interpret the anion gap in practice
Reading the anion gap requires more than checking a single number. Albumin has a major role because it is a negatively charged protein that contributes significantly to the gap. If albumin is low, the measured anion gap may seem falsely normal or only mildly elevated even when important acids are present.
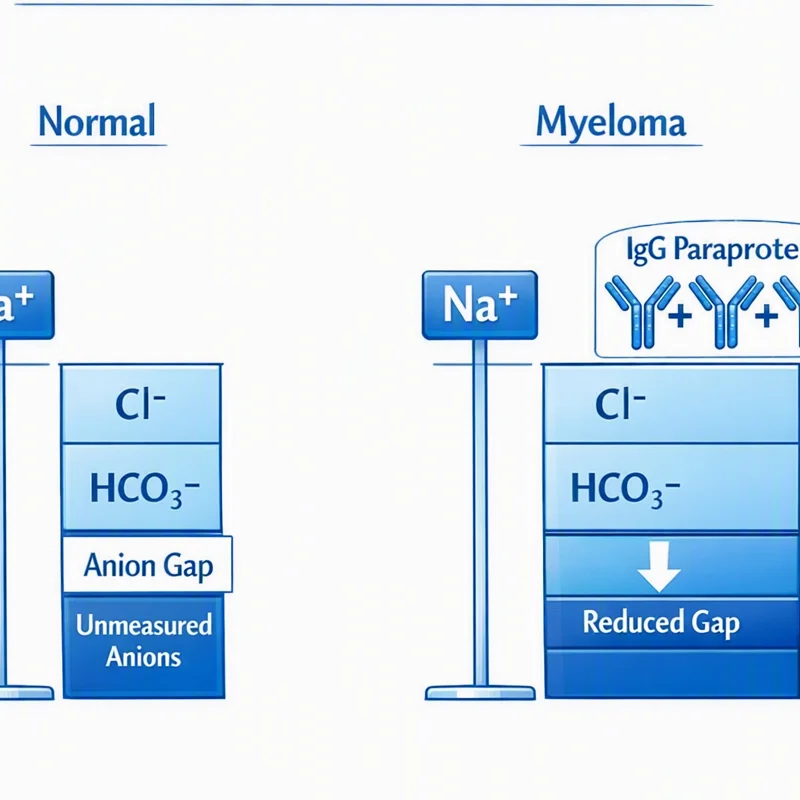
That is why a corrected anion gap is often more useful than the raw value. Adjusting for albumin enhances lab interpretation and helps reduce missed diagnoses in patients with critical illness, malnutrition, liver disease, or inflammation. A lower albumin level can mask a clinically important acid load.
Another useful concept is the delta gap, which compares against the change in anion gap to the change in bicarbonate. This helps reveal whether another acid-base disorder is also present. For example, a patient may have a high anion gap metabolic acidosis plus a second process such as metabolic alkalosis or normal-gap acidosis.
Clinical context also includes the rest of the lab values. A rising creatinine may support renal failure, a high lactate can support tissue hypoperfusion, and positive ketones can support ketoacidosis. The anion gap is strongest when it is integrated with the patient’s symptoms, history, exam findings, and full electrolyte picture.
When a normal anion gap can still be dangerous
A typical anion gap does not guarantee safety. Significant illness can still be hiding even if the number appears acceptable. For example, diarrhea can result in significant bicarbonate loss and a normal-gap metabolic acidosis that results in acidemia. The patient may be very ill despite a gap that is not elevated.
Renal tubular acidosis is another key cause of normal anion gap acidosis. In this condition, the kidneys cannot properly manage acid or bicarbonate handling. Patients may present with weakness, dehydration, or electrolyte abnormalities that call for treatment even though the anion gap does not stand out.
A mixed acid-base disorder can also conceal a dangerous process. One disorder may raise the gap while another lowers it, creating a value that looks normal on paper. For example, a patient may have lactic acidosis plus metabolic alkalosis, or a high-gap process plus chloride-driven acidosis. In such cases, the anion gap alone can fail to show the full picture.
Chloride is central to recognizing these cases because increased chloride often accompanies bicarbonate loss. If the clinician only sees a normal anion gap, the underlying problem may be ignored. This is why the electrolyte pattern must always be read as a single unit, not in isolation.
Why the anion gap is useful for prioritization and care decisions
In urgent care, the anion gap helps clinicians determine who needs faster escalation. A significantly elevated gap may indicate a life-threatening process requiring immediate review in critical care. Even before the exact cause is known, the result can justify prompt testing, careful monitoring, or ICU-level concern.
The gap also supports early diagnosis. If the clinical picture suggests sepsis, shock, diabetic crisis, poisoning, or renal failure, the anion gap helps confirm that a metabolic process is underway. This can expedite treatment choices such as fluid resuscitation, toxin-specific therapy, insulin, dialysis consultation, or repeat assessment of acid-base status.
For monitoring, serial anion gaps can help track whether a treatment is working. If the cause is corrected, the gap may decrease as the underlying acid load falls. That trend can be especially helpful in patients with acidemia who are too unstable to wait for slower clinical changes.
Because the anion gap is available from common chemistry testing, it is a practical tool for bedside decisions. It does not replace the exam or more advanced testing, but it gives emergency teams a fast way to triage the sickest patients and to direct the next diagnostic step.
Limitations of anion gap interpretation
Even though helpful, the anion gap is not foolproof. A testing error can create a misleading result, which is why a repeat test is sometimes necessary if the number does not match the overall clinical picture. Problems with sample handling, sample contamination, or transcription problems can all alter interpretation.
The specified normal range further matters. Different laboratories may use slightly different methods and normal values, so clinicians must read the result according to the reporting lab. A value that looks mildly abnormal in one setting may be normal in another.
The measure is also limited because it estimates only some of the chemistry in the blood. Unmeasured ions may build up, but the tool cannot identify them directly. It can suggest their presence in the body, yet it cannot specify the exact substance causing the change. That is why the anion gap is a hint, not a complete solution.
Finally, clinical circumstances always counts. Someone with nausea and vomiting, diabetes, kidney disease, suspected poisoning, or infection may need further workup no matter whether the anion gap is high, normal, or borderline. The best interpretation integrates the calculated value with symptoms, exam findings, and the broader metabolic picture.
FAQ about anion gap in emergency care
How does the anion gap show in emergency care?
The anion gap helps tell emergency providers whether there may be a hidden acid-base issue that is not clear from routine chemistry alone. It is a fast way to look for metabolic acidosis, unmeasured anions, and potential causes such as lactic acidosis, ketoacidosis, renal failure, or toxin exposure. In practice, it assists refine the differential diagnosis and direct urgent next steps.
Why is the anion gap important for diagnosing metabolic acidosis?
The anion-gap result is significant because it can separate various types of metabolic acidosis. A increased anion gap suggests added acids are building up, while a typical anion gap indicates bicarbonate loss or chloride gain. This distinction enhances diagnostic value and helps clinicians target the underlying cause more promptly.
Can a standard anion gap still indicate a serious condition?
Indeed. A standard anion gap can still be seen in significant illnesses such as diarrhea, renal tubular acidosis, or a mixed acid-base disorder. A patient may still have marked acidemia even if the gap is not elevated. That is why ER clinicians interpret the anion gap alongside symptoms, lab values, and the overall clinical picture.
How does albumin affect the anion gap?
This protein lowers or raises the expected anion gap because it is a major unmeasured anion in the blood. When albumin is low, the measured anion gap may appear deceptively normal. A corrected anion gap adjusts for that effect and gives a more precise estimate of the patient’s acid load.
What causes a high anion gap in the emergency setting?
Common causes include lactic acidosis from sepsis or shock, ketoacidosis, renal failure, toxic alcohols, and salicylate poisoning. These conditions can create a dangerous metabolic derangement that requires prompt recognition. The anion gap calculator helps clinicians notice the pattern early and guide the workup.